


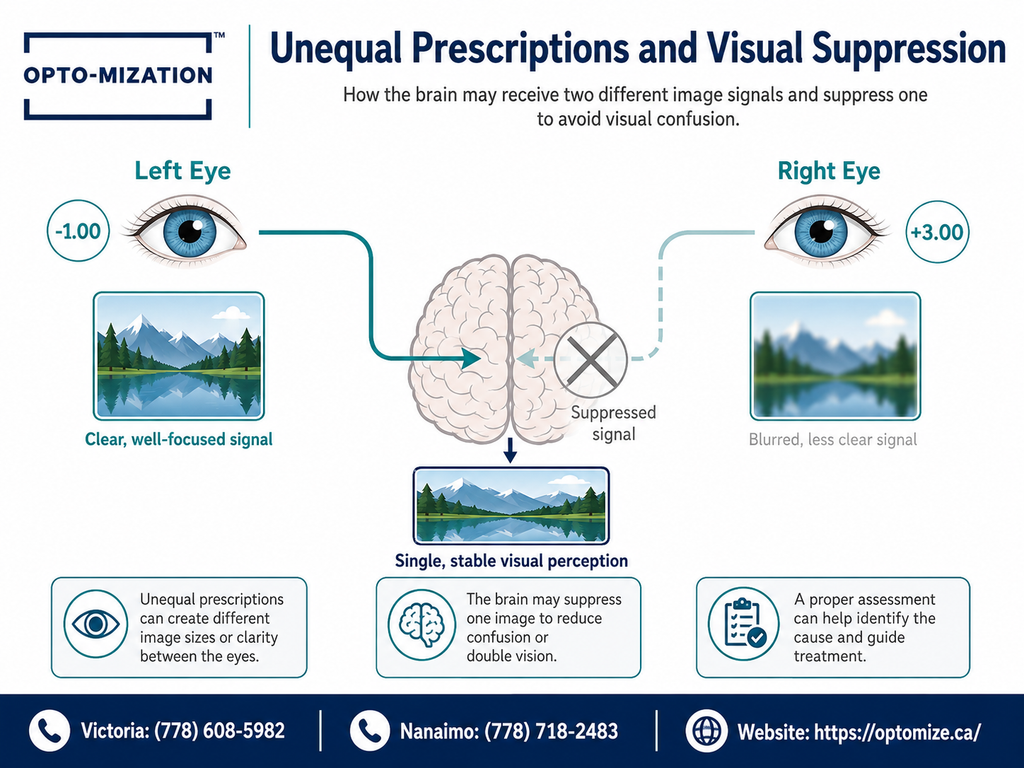
Anisometropia means each eye has a meaningfully different prescription, and glasses or contacts alone often cannot resolve the full problem. When the brain receives two signals of different clarity, it frequently suppresses the weaker one, and that suppression can lead to one eye staying persistently blurry even with corrective lenses in place. Vision therapy addresses the underlying coordination failure directly, retraining the visual system to integrate input from both eyes rather than favoring one.
Key Takeaways
- Anisometropia creates an unequal visual signal between eyes, which the brain often resolves by suppressing the weaker eye.
- Correction with glasses or contacts is necessary but frequently insufficient on its own when suppression is already established.
- Vision therapy targets the brain’s processing of binocular signals, not the optical prescription itself.
- Children benefit most from early intervention, but adults can also achieve meaningful improvement with a structured program.
- A functional eye exam is the starting point for determining whether vision therapy is appropriate for a given case.
- Results depend on consistent participation; most structured programs run over several months with weekly in-office sessions.
Things You Must Know
1. Suppression Develops Quietly and Becomes Self-Reinforcing
When one eye consistently sends a blurrier image, the brain learns to discount that eye’s input to avoid visual confusion. Over time, this suppression becomes a learned pattern, not just an optical issue. Correcting the prescription with new glasses can actually cause temporary discomfort or double vision at first, because the brain has been ignoring one eye’s signal for so long that suddenly receiving two clear images feels unfamiliar. Vision therapy works through this phase in a structured, guided way.
2. Amblyopia Is a Common Secondary Consequence
Anisometropic amblyopia, sometimes called “lazy eye,” develops when the suppressed eye loses visual acuity from disuse rather than from any structural problem with the eye itself. The eye is healthy; the brain simply stopped developing that visual pathway. Patching the stronger eye is one traditional approach, but vision therapy can address the binocular integration component more directly, particularly in cases where patching alone has not produced lasting improvement.
3. The Prescription Must Be Stabilized Before Therapy Begins
Vision therapy produces the best outcomes when the optical correction is already optimized. If a child or adult enters therapy with an outdated or incorrect prescription, the exercises cannot accurately challenge the visual system. An updated comprehensive eye exam, and often a functional eye exam that goes beyond standard acuity testing, should precede any formal therapy program.
What Actually Happens During Vision Therapy for Anisometropia?
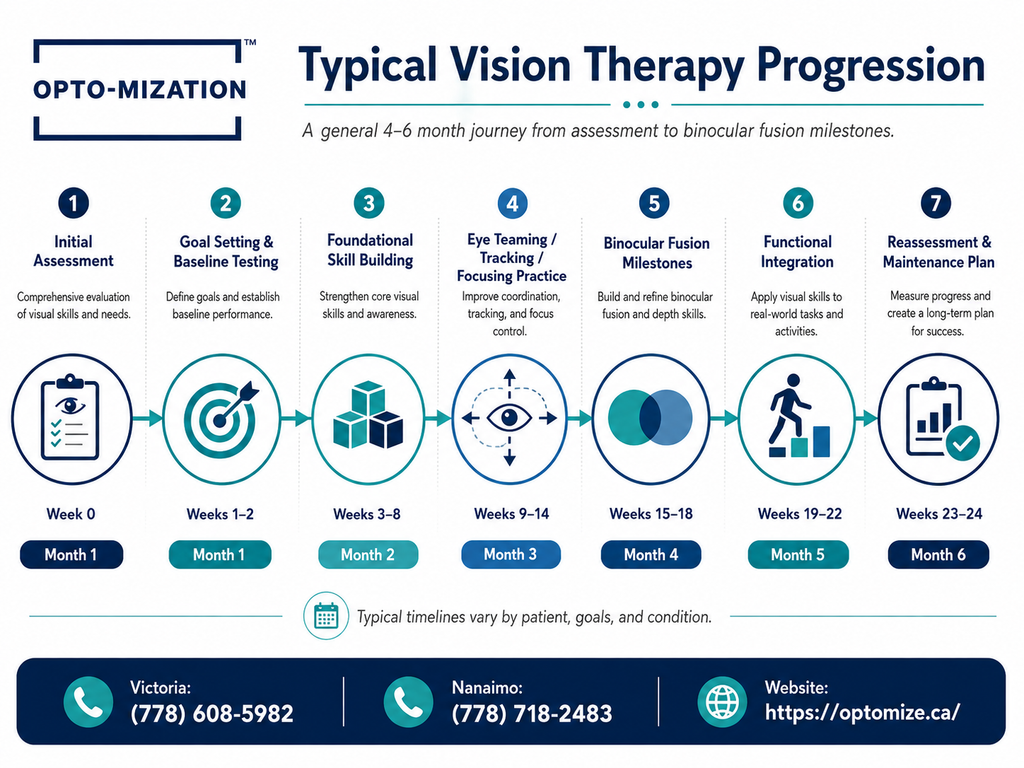
Vision therapy is a structured program of exercises and activities designed by a developmental or neuro-optometrist to improve how the eyes and brain communicate. For anisometropia specifically, the program focuses on reducing suppression and building binocular fusion, the ability to combine the images from both eyes into one clear, stable, three-dimensional perception.
Sessions typically take place weekly in-clinic and are supplemented with daily home exercises. A therapist guides the patient through activities using specialized lenses, prisms, filters, and sometimes computer-based tools. The exercises progressively challenge the visual system to accept and process the previously suppressed eye’s signal.
Research on vision therapy for anisometropic amblyopia suggests that combining optical correction with active binocular therapy can produce gains in visual acuity and stereo vision beyond what patching alone achieves, particularly in school-age children. A peer-reviewed study in children aged 7–10 found that vision therapy combined with conventional treatment produced significantly greater visual acuity improvement than optical correction and patching alone, with gains maintained after therapy ended.
How Does a Functional Eye Exam Differ from a Standard One?
A standard eye exam measures visual acuity and determines the optical prescription. A functional eye exam goes further, evaluating how well both eyes work together, how efficiently they focus at different distances, how accurately they track and converge, and how the brain processes visual information. For anisometropia, the functional exam reveals whether suppression is present, how deep it is, and what binocular vision skills need direct attention.
This distinction matters when choosing a treatment path. A patient might have 20/20 vision in each eye individually and still experience headaches, reading fatigue, or poor depth perception because the two eyes are not coordinating effectively. The functional exam surfaces these issues.
Vision Therapy vs. Patching vs. Glasses: Understanding the Options
| Approach | Primary Goal | Best Suited For | Limitation |
| Glasses / Contact Lenses | Correct optical prescription difference | All anisometropia cases as a baseline | Does not address existing suppression or poor binocular fusion |
| Patching (Occlusion Therapy) | Force use of the weaker eye | Younger children with amblyopia | Can improve acuity in the weaker eye but does not directly build binocular cooperation |
| Vision Therapy | Build binocular integration and reduce suppression | Children and adults with suppression, amblyopia, or poor fusion despite correction | Requires consistent participation over months; outcomes vary by case severity |
| Combined (Glasses + Vision Therapy) | Correct optics and retrain binocular processing simultaneously | Moderate to complex anisometropia with established suppression | Higher time commitment; may require specialist access |
Who Benefits Most from Vision Therapy for Anisometropia?
Children between the ages of four and twelve tend to show the strongest response because the visual cortex retains significant plasticity during this period. Earlier detection generally translates to shorter treatment timelines and more durable outcomes. That said, neuroplasticity persists into adulthood, and many adults with long-standing anisometropia experience meaningful improvement in comfort, depth perception, and visual stamina through therapy.
Studies examining adult amblyopia treatment outcomes have found measurable improvements in visual acuity and binocular function in adult patients who completed structured vision therapy programs. A prospective study of adults with anisometropic amblyopia found significant improvement in best-corrected visual acuity after active vision therapy, challenging the earlier clinical assumption that treatment after age twelve produces no benefit.
Adults who report eye strain after reading, difficulty with tasks that require depth judgment, or persistent blurriness in one eye despite an updated prescription are strong candidates for a functional evaluation. The eyes feeling tired despite correct lenses is one of the clearest signals that something beyond the prescription needs attention.
What a Typical Vision Therapy Program Looks Like
- Functional Eye Exam: The optometrist measures binocular function, suppression depth, stereopsis, and accommodation in addition to the standard prescription assessment.
- Individualized Program Design: Based on the exam findings, the therapist builds a sequence of activities targeted at the specific deficits identified. No two programs are identical.
- Weekly In-Office Sessions: Each session runs roughly 45 to 60 minutes. The therapist introduces new challenges as the visual system responds and adjusts.
- Daily Home Exercises: Short practice sessions between clinic visits reinforce what was covered in-office. Consistency here significantly affects the pace of progress.
- Progress Reassessments: Periodic re-examinations track objective gains in acuity, fusion, and stereopsis, and allow the program to be adjusted accordingly.
- Graduation and Monitoring: Once therapy goals are met, the optometrist establishes a monitoring schedule to confirm that gains are maintained over time.
Vision therapy programs for amblyopia and binocular vision dysfunction are individualized rather than fixed in length, with program duration varying based on the nature and severity of each case. The College of Optometrists in Vision Development describes optometric vision therapy as conducted under the supervision of an optometrist and supported by ongoing, evidence-based scientific research, with treatment designed to retrain the learned aspects of vision through neuroplasticity rather than following a one-size-fits-all protocol.
Common Mistakes to Avoid
- Stopping after glasses alone show partial improvement. Many patients see a noticeable acuity gain after getting the right prescription and assume the problem is resolved. If suppression remains, the visual system is still not functioning as a cooperative unit.
- Skipping home exercises. In-office sessions introduce skills; home practice builds them. Patients who skip daily exercises consistently show slower progress and more frequent plateaus.
- Delaying evaluation in children because “they seem fine.” Children with anisometropia rarely complain of blurry vision because their brain has already adapted by suppressing one eye. Behavioral signals, like covering one eye, tilting the head, or avoiding reading, warrant a functional exam even when the child does not report visual discomfort.
- Assuming adult treatment won’t work. Age is a factor in treatment speed, not a hard barrier to improvement. Adults who commit to a structured program regularly achieve gains in comfort, depth perception, and reading endurance.
- Choosing a provider based on proximity alone. Vision therapy requires a developmental or neuro-optometrist with specific training in binocular vision. A standard optometry practice offering occasional eye exercises is not the same level of care.

How Anisometropia Affects Learning and Daily Function
For children, untreated anisometropia with suppression often surfaces as an academic struggle rather than a visual complaint. A child avoiding reading despite knowing the words may be dealing with a visual system that makes sustained close-up work genuinely uncomfortable, not a motivation or learning problem. The binocular vision demand of reading, where both eyes must converge precisely on a moving line of text, can be taxing when one eye’s input is being suppressed or marginalized.
Adults experience similar patterns in different contexts: difficulty with tasks that require depth judgment, fatigue after screen work, or a persistent sense of visual effort that no prescription change seems to resolve. These are functional symptoms that point toward binocular dysfunction rather than a simple refractive error.
| Symptom | Possible Connection to Anisometropia |
| One eye consistently blurrier | Suppression or uncorrected prescription difference |
| Headaches after reading or screen use | Eyes working against each other to maintain focus |
| Poor depth perception | Reduced stereopsis from limited binocular fusion |
| Child avoiding close-up work | Binocular demand of near tasks triggering visual discomfort |
| Eye fatigue despite correct glasses | Optical correction alone not addressing fusion deficit |
Frequently Asked Questions
Why are ophthalmologists against vision therapy?
Not all ophthalmologists oppose vision therapy, but skepticism among some in the field comes from the historical emphasis on surgical and pharmaceutical interventions, and from variability in research quality across different vision therapy studies. The American Academy of Ophthalmology has expressed reservations about certain applications, while optometric organizations point to a substantial body of peer-reviewed evidence supporting its use for conditions like convergence insufficiency and amblyopia. The divide is partly jurisdictional and partly reflects genuinely different clinical training backgrounds. Seeking a second opinion from a developmental optometrist is reasonable when ophthalmological advice contradicts optometric recommendations.
Will insurance pay for vision therapy?
Coverage varies considerably by insurer, plan type, and country. In Canada, some extended health benefits plans cover vision therapy services, often up to a set annual maximum, when billed by a licensed optometrist. Medical plans do not typically cover vision therapy unless it follows a diagnosed neurological condition. Contacting your insurer directly with the relevant billing codes before starting a program gives you the clearest picture of what will be reimbursed.
Can I do vision therapy on my own?
Some apps and online exercise programs offer home-based visual training, and these can serve as useful supplements to a supervised program. Doing them in place of professional therapy for anisometropia is a different matter. Anisometropia with suppression requires individualized assessment to determine which exercises are appropriate and at what difficulty level. Poorly calibrated home exercises can reinforce the wrong patterns or fail to progress the visual system at all. Home exercises prescribed as part of a supervised program produce far better outcomes than self-directed alternatives.
Should I wear glasses if I have anisometropia?
Optical correction is the foundation of any anisometropia treatment plan. Without glasses or contact lenses that equalize the prescription as much as possible, the visual system continues to receive unbalanced input, making any therapeutic work harder to sustain. Some people with large prescription differences find contact lenses more comfortable than glasses because contacts eliminate the image size difference that strong corrective lenses produce. Your optometrist can help determine which form of correction gives your visual system the best starting point for therapy.
Can anisometropia go away?
Anisometropia is a refractive condition, meaning it reflects a structural difference in how each eye focuses light. The prescription difference itself does not typically disappear without intervention. In children, prescriptions continue to change through adolescence, and in some cases the difference between eyes may decrease naturally as the visual system matures. In adults, the refractive state is more stable. What vision therapy addresses is not the prescription difference but the brain’s learned response to it, specifically the suppression and binocular dysfunction that compound the underlying optical issue.
Taking the Next Step
Glasses correct what you see. Vision therapy works on how your brain processes what both eyes send it together. For anyone dealing with persistent blurriness in one eye, reading fatigue, or a child showing behavioral signs of visual difficulty, a functional evaluation is the clearest way to understand what is actually driving the problem.
Opto-Mization offers vision therapy programs designed around individual functional assessments, not generic protocols. If you are in the Nanaimo area or surrounding region and want to know whether vision therapy is the right path for your situation, reach out to the Opto-Mization team to schedule a comprehensive functional eye exam. The assessment is where every productive conversation about treatment begins.

